
Inotropic drug responses in human 3D in vitro cardiac microtissues
White Paper | SmartHeart® Contractility Assay
4Dcell Scientific Team | Updated October 2026 | Based on the SmartHeart Contractility Assay qualification study.
Explore how human 3D cardiac microtissues respond to positive and negative inotropic compounds through quantitative measurements of contraction strain, contraction and relaxation kinetics, and beating activity.
SmartHeart® combines human iPSC-derived cardiomyocytes and cardiac fibroblasts in self-assembled ring-shaped tissues, enabling multiparametric assessment of drug-induced cardiac mechanical responses in a 96-well format.
Recording conditions: Day 21 post-seeding • Spontaneous beating • 0.6 mM Ca²⁺ Tyrode's solution for positive inotropes and 2 mM Ca²⁺ for negative inotropes • Brightfield videos acquired at 40 fps for 12 seconds • Acute sequential compound addition with a 4-minute incubation before each acquisition.
-
HIGHLIGHTS
→ Multiparametric contractility profiling combines beating frequency, contraction strain, maximum contraction speed and maximum relaxation speed to characterize compound-specific functional responses.
→ Ring-shaped 3D cardiac architecture enables coordinated tissue-level contraction around a deformable hydrogel pillar, providing quantitative mechanical readouts in a defined three-dimensional geometry.
→ Functional assessment at Day 21 post-seeding provides a standardized experimental window for characterizing β-adrenergic responses, calcium-channel modulation and sarcomeric drug effects in human cardiac microtissues.
→ Low-calcium Tyrode conditions (0.6 mM Ca²⁺) establish a submaximal calcium environment, increasing the dynamic range available for detecting positive inotropic responses.
→ Isoprenaline induces both positive inotropy and chronotropy in SmartHeart®, demonstrating coordinated β-adrenergic modulation of contraction strain and spontaneous beating frequency.
→ Fit-for-purpose assay qualification across seven reference compounds demonstrates correct identification of five positive and two negative inotropic responses, with three independent experiments per compound and characterized assay sensitivity.
-
SUMMARY
Evaluating drug-induced changes in cardiac contractility is essential for both cardiovascular drug discovery and preclinical cardiac safety assessment. Positive and negative inotropic effects may arise through different pharmacological mechanisms, including adrenergic receptor activation, calcium-channel modulation, sarcomeric regulation, and ion-channel inhibition.
This white paper presents the characterization of inotropic drug responses using SmartHeart®, a human 3D cardiac microtissue platform developed by 4Dcell.
Self-assembled cardiac rings composed of human iPSC-derived cardiomyocytes and cardiac fibroblasts were evaluated at Day 21 after seeding. Drug responses were quantified from brightfield recordings using automated image analysis.
A panel of seven reference compounds was investigated: isoproterenol, Bay K 8644, omecamtiv mecarbil, istaroxime, phenylephrine, itraconazole, and quinidine.
The SmartHeart® Contractility Assay correctly identified the expected direction of the inotropic response for all seven reference compounds under the qualified experimental conditions. Concentration-response analysis also characterized compound potency, beating frequency responses, and contraction–relaxation kinetics.
These results support the use of SmartHeart® for fit-for-purpose screening and characterization of drug-induced changes in human cardiac contractility, within the method's established operating conditions and limitations.
-
INTRODUCTION
Why assess inotropic drug effects in human cardiac models?
Cardiac contractility results from the coordinated interaction of electrical excitation, intracellular calcium regulation, sarcomeric activation, and mechanical tissue properties.
Pharmacological compounds can alter cardiac mechanical activity through several distinct mechanisms. Positive inotropic agents increase myocardial contractile performance, whereas negative inotropic agents reduce it. These effects may occur independently of changes in heart rate or electrophysiological parameters.
Accurate assessment of drug-induced inotropy is therefore relevant to both therapeutic development and cardiac safety evaluation.
In cardiovascular drug discovery, contractility measurements help characterize compounds intended to improve or modulate cardiac mechanical function. In safety pharmacology, they help identify unintended changes in contraction or relaxation that may not be apparent from ion-channel measurements alone.
A human cardiac model capable of quantifying multiple mechanical parameters can provide complementary information on compound activity and help guide further mechanistic investigation.
SmartHeart®: a human 3D cardiac tissue model
SmartHeart® is a 96-well platform designed to generate self-assembled, ring-shaped human cardiac microtissues.
Each cardiac ring is formed from human induced pluripotent stem cell-derived cardiomyocytes and cardiac fibroblasts. The tissue develops around a deformable hydrogel pillar, creating a defined mechanical geometry that enables quantitative analysis of contraction-induced deformation.
Unlike measurements based exclusively on electrical signals or unconstrained cellular motion, SmartHeart® quantifies the mechanical response of a three-dimensional cardiac tissue.
The platform enables simultaneous analysis of several parameters, including:
-
Contraction strain
-
Derived contractile stress
-
Mean and maximum contraction speeds
-
Mean and maximum relaxation speeds
-
Contraction and relaxation times
-
Spontaneous beating frequency and regularity
These complementary readouts support the characterization of compound-specific cardiac functional responses.

Figure 1. SmartHeart® human 3D cardiac microtissues form ring-shaped structures around deformable hydrogel pillars. Tissue deformation is tracked from brightfield recordings to quantify contraction strain, beating activity, and contraction–relaxation kinetics.
-
METHODOLOGY
Cardiac tissue generation and experimental conditions
SmartHeart® cardiac microtissues were generated by co-culturing human iPSC-derived cardiomyocytes and primary human ventricular cardiac fibroblasts at a 3:1 ratio.
Experiments were performed at Day 21 after seeding, using spontaneously beating cardiac tissues.
The qualification study followed a defined experimental workflow:
-
Tissue format: SmartHeart® 96-well plate containing ring-shaped cardiac microtissues.
-
Cell composition: Human iPSC-derived cardiomyocytes and human ventricular cardiac fibroblasts.
-
Tissue maturation: Day 21 after seeding.
-
Compound exposure: Sequential, cumulative concentration additions.
-
Incubation: Four minutes before each acquisition.
-
Vehicle control: DMSO baseline, with a maximum cumulative concentration of 0.1%.
-
Video acquisition: 12-second brightfield recordings at 40 frames per second.
-
Data analysis: SmartX™ image analysis and contractility feature extraction.
Two extracellular calcium conditions were used to establish an appropriate dynamic range for detecting positive and negative inotropic effects.
Positive inotropic compounds were evaluated in low-calcium Tyrode's solution (0.6 mM Ca²⁺), whereas negative inotropic compounds were evaluated in high-calcium Tyrode's solution (2 mM Ca²⁺).
The low-calcium condition provides a submaximal extracellular calcium environment suitable for assessing increases in contractile response. The higher-calcium condition supports the detection of reductions in tissue contractility.
Quantitative analysis of cardiac contractility
Contractile activity was quantified by tracking changes in the geometry of individual cardiac rings during spontaneous beating.
The SmartX™ analysis pipeline extracts time-resolved deformation signals from brightfield videos and calculates multiple morphological and contractility parameters.
Contraction strain describes the relative deformation of the cardiac ring during a contraction cycle. Together with contraction and relaxation speeds, it provides a quantitative description of the tissue's mechanical response to compound exposure.
Contraction strain is a deformation-based readout and should not be interpreted as a direct measurement of absolute myocardial force. Mechanical stress can be derived using the characterized mechanical properties of the hydrogel pillar.
For each compound, responses were normalized to the corresponding ring's own vehicle baseline and analyzed across the tested concentration range.
Reference compounds and study design
Seven compounds with established positive or negative inotropic activity were selected to investigate the assay's pharmacological response across different mechanisms of action.
The panel included five positive inotropes (isoproterenol, Bay K 8644, omecamtiv mecarbil, istaroxime, and phenylephrine) and two negative inotropes (itraconazole and quinidine).
Each compound was assessed across three independent experiments, with at least 20 evaluable cardiac microtissues contributing to the concentration-response analysis.
Statistical analysis included concentration-specific comparisons with vehicle baseline and global directional analyses of the dose-response profiles.
-
OVERVIEW OF INOTROPIC DRUG RESPONSES
The SmartHeart® Contractility Assay was evaluated using seven reference compounds representing distinct pharmacological mechanisms. All compounds produced the expected direction of inotropic response under the tested conditions.
Compound
Isoproterenol
Bay K 8644
Omecamtiv mecarbil
Istaroxime
Phenylephrine
Itraconazole
Quinidine
Inotropic response
Positive ↑
Positive ↑
Positive ↑
Positive ↑
Positive ↑
Negative ↓
Negative ↓
Tissues (n)
25
27
21
22
30
42
28
-
RESULTS: POSITIVE INOTROPIC RESPONSES
All contraction strain values are normalized to the corresponding tissue's DMSO baseline and expressed as fold change.
Curves represent mean responses, with standard deviation (SD) and standard error of the mean (SEM) indicated on the graphs.
Isoproterenol — β-Adrenergic Receptor Activation
Isoproterenol (isoprenaline) is a non-selective β-adrenergic receptor agonist that stimulates cardiac contractile activity and increases beating frequency.
In SmartHeart® cardiac microtissues, isoproterenol induced a concentration-dependent increase in contraction strain and spontaneous beating frequency.
Increases in contraction and relaxation speeds were also observed, consistent with a coordinated positive inotropic and chronotropic response.
The measured EC50 for contraction strain was 35.7 nM, within the range of published values obtained from human cardiac preparations under different experimental conditions.
These results demonstrate that SmartHeart® detects β-adrenergic modulation of both tissue contractility and spontaneous beating activity.
The concurrent increases in frequency and contraction strain should not, however, be interpreted as direct evidence of a positive force-frequency relationship, which requires controlled variation of stimulation frequency.

Figure 2. Isoproterenol concentration-response in SmartHeart® cardiac microtissues, showing increased contraction strain. n = 25 microtissues; N = 3 independent experiments. Day 21, 0.6 mM Ca²⁺ Tyrode's solution.
Bay K 8644 — L-Type Calcium Channel Activation
Bay K 8644 is an activator of L-type calcium channels, which contribute to excitation–contraction coupling in cardiomyocytes.
In SmartHeart®, Bay K 8644 induced a significant positive inotropic response, characterized by increased contraction strain across the tested concentration range.
Interestingly, the increase in contractile activity was accompanied by a reduction in spontaneous beating frequency.
This distinct response illustrates how changes in tissue contractility and beating rate can occur in opposite directions following pharmacological modulation.
The results are consistent with the expected positive inotropic action of L-type calcium-channel activation. However, the mechanisms underlying the observed reduction in spontaneous beating frequency were not directly investigated in this study.

Figure 3. Concentration-dependent increase in contraction strain following L-type calcium channel activation by Bay K 8644, demonstrating a positive inotropic response. n = 27 microtissues; N = 3 independent experiments. Day 21, 0.6 mM Ca²⁺ Tyrode's solution.
Omecamtiv Mecarbil — Direct Cardiac Myosin Activation
Omecamtiv mecarbil is a cardiac myosin activator that modulates sarcomeric function and increases contractile performance through a mechanism distinct from direct calcium-channel activation.
In SmartHeart® microtissues, omecamtiv mecarbil produced a significant positive inotropic response, with contraction strain increasing across the pharmacologically active concentration range.
The measured EC50 for contraction strain was 519 nM, close to a published biochemical reference value of approximately 520 nM obtained using recombinant human β-cardiac myosin. These values were measured using different experimental endpoints and should not be considered directly interchangeable.
Unlike isoproterenol, omecamtiv mecarbil did not produce a statistically supported sustained directional change in beating frequency across the tested concentration range.
The compound also modified contraction and relaxation kinetics, demonstrating that increased contraction strain does not necessarily correspond to faster tissue contraction.
At the highest tested concentration (3 µM), the contractile response declined relative to its maximum observed response, alongside increased beat-to-beat irregularity at that concentration.
These findings illustrate the value of multiparametric contractility measurements for characterizing concentration-dependent changes in cardiac mechanical function. The high-concentration response requires complementary investigation before attributing it to cytotoxicity or a specific cellular stress mechanism.

Figure 4. Positive inotropic response to omecamtiv mecarbil, characterized by increased contraction strain followed by partial attenuation at the highest tested concentration (3 µM). n = 21 microtissues; N = 3 independent experiments. Day 21, 0.6 mM Ca²⁺ Tyrode's solution.
Istaroxime — Modulation of Cardiac Inotropy and Relaxation
Istaroxime is a pharmacological compound with reported actions involving Na⁺/K⁺-ATPase inhibition and SERCA2a activation.
These mechanisms make it particularly relevant for investigating contractile activity and relaxation-associated cardiac function.
In SmartHeart® cardiac microtissues, istaroxime produced a significant positive inotropic response, as demonstrated by increased contraction strain.
Changes in contraction and relaxation kinetics were also observed, providing a broader description of the compound's functional profile than contraction amplitude alone.
No statistically supported sustained directional change in beating frequency was identified across the tested concentration range.
The observed mechanical responses are compatible with the compound's known pharmacology. However, the contractility measurements alone cannot establish whether the changes in relaxation result from altered intracellular calcium reuptake, myofilament properties, or their combined effects.
Complementary calcium-transient measurements would be required for a more direct mechanistic assessment.

Figure 5. Concentration-dependent increase in contraction strain induced by istaroxime, demonstrating a positive inotropic response in SmartHeart® cardiac microtissues. n = 22 microtissues; N = 3 independent experiments. Day 21, 0.6 mM Ca²⁺ Tyrode's solution.
Phenylephrine — α1-Adrenergic Receptor Activation
Phenylephrine is an α1-adrenergic receptor agonist that can modulate cardiac contractility through receptor-mediated signaling pathways.
In SmartHeart® cardiac microtissues, phenylephrine produced a significant concentration-dependent increase in contraction strain.
A positive chronotropic response was also detected under the tested conditions.
The measured EC50 for contraction strain was 0.569 µM, indicating greater apparent potency than the human ventricular trabeculae reference identified in the qualification literature review (12.3 µM).
This difference highlights the importance of accounting for experimental conditions, tissue preparations, and model-specific pharmacological sensitivity when comparing potency values.

Figure 6. Concentration-dependent increase in contraction strain following α1-adrenergic receptor activation by phenylephrine, demonstrating a positive inotropic response. n = 30 microtissues; N = 3 independent experiments. Day 21, 0.6 mM Ca²⁺ Tyrode's solution.
-
RESULTS: NEGATIVE INOTROPIC RESPONSES
Itraconazole — Drug-Induced Reduction in Cardiac Contractility
Itraconazole is an antifungal compound with documented effects on cardiac function, including inhibition of L-type calcium current.
In SmartHeart®, itraconazole produced a significant negative inotropic response, with contraction strain decreasing across the tested concentration range.
A negative chronotropic response was also detected.
The measured IC50 for contraction strain was 914 nM.
These findings demonstrate the ability of the SmartHeart® Contractility Assay to identify drug-induced reductions in cardiac mechanical activity.
Although published experimental studies support the cardiac depressant effects of itraconazole, directly comparable human myocardial contractility potency data were not identified in the qualification literature review.
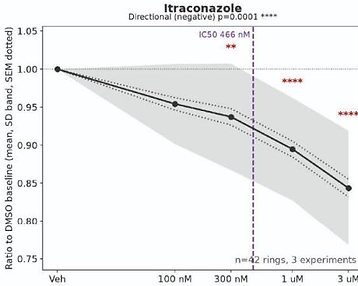
Figure 7. Concentration-dependent reduction in contraction strain induced by itraconazole, demonstrating a negative inotropic response in SmartHeart® human 3D cardiac microtissues. n = 42 microtissues; N = 3 independent experiments. Day 21, 2 mM Ca²⁺ Tyrode's solution.
Quinidine — Ion-Channel Modulation and Negative Inotropy
Quinidine is an antiarrhythmic compound with effects on multiple cardiac ion channels, including sodium channels.
In SmartHeart® cardiac microtissues, quinidine induced a significant reduction in contraction strain, consistent with a negative inotropic effect.
A negative chronotropic response was also observed across the tested concentration range.
The measured IC50 for contraction strain was 1.31 µM.
These findings illustrate how a compound primarily characterized for its electrophysiological activity can also produce a measurable alteration in cardiac tissue mechanics.
Combining contractility measurements with complementary electrophysiological assays may help characterize the mechanisms underlying such responses.

Figure 8. Concentration-dependent reduction in contraction strain induced by quinidine, demonstrating a negative inotropic response in SmartHeart® human 3D cardiac microtissues. n = 28 microtissues; N = 3 independent experiments. Day 21, 2 mM Ca²⁺ Tyrode's solution.
-
ASSAY PERFORMANCE: REPRODUCIBILITY AND SENSITIVITY
Beyond detecting the expected pharmacological responses, the qualification study characterized the variability and sensitivity of the SmartHeart® Contractility Assay.
Reproducibility across independent experiments
Variability was evaluated at the individual cardiac ring and independent-experiment levels.
Isoproterenol was used as a representative positive inotropic reference compound to characterize the reproducibility of normalized contractility responses.
Across the four concentrations tested, the experiment-to-experiment coefficients of variation remained below 10% for both beating frequency and contraction strain.
These findings support reproducible measurement of the pharmacological response under the qualified experimental conditions.
Minimum Detectable Effect of contractility readouts
The Minimum Detectable Effect (MDE) estimates the smallest true response that the statistical analysis can reliably detect under a specified experimental design.
For the qualified SmartHeart® Contractility Assay, the following MDE values were established:
-
Beating frequency: 3.7%
-
Contraction strain: 5.5%
-
Mean contraction speed: 4.5%
-
Mean relaxation speed: 5.7%
These values were derived from the variability observed across the reference compound panel, assuming at least 20 evaluable cardiac microtissues, three independent experiments, 80% statistical power, a 5% significance level, and an effect present at approximately half of the tested concentration levels.
The MDE values are specific to the qualified experimental design and should not be interpreted as universal detection thresholds for every compound, protocol, or individual concentration.
A compound producing no statistically supported response under these conditions should therefore be described as showing no detectable effect within the assay's sensitivity, concentration range, and exposure window, rather than being considered definitively inactive.
-
DISCUSSION: WHAT DO THESE INOTROPIC RESPONSES REVEAL?
Distinguishing inotropy from chronotropy
Changes in beating frequency and contraction amplitude do not necessarily follow the same pharmacological response.
The SmartHeart® reference compound panel illustrates this distinction.
Isoproterenol increased both contraction strain and spontaneous beating frequency, whereas Bay K 8644 increased contraction strain while reducing beating frequency.
Omecamtiv mecarbil produced a positive inotropic response without a statistically supported sustained directional change in beating frequency.
These distinct signatures demonstrate the importance of measuring cardiac mechanical activity and beating behavior independently.
However, simultaneous increases in spontaneous beating frequency and contraction strain do not, by themselves, establish a positive force-frequency relationship. Demonstrating rate-dependent modulation of force requires a dedicated protocol using controlled stimulation frequencies.
Why multiparametric contractility measurements matter
A compound's effects on cardiac mechanical function cannot always be summarized by a single contractility parameter.
Contraction strain characterizes the magnitude of tissue deformation, while contraction and relaxation speeds describe the kinetics of the mechanical response.
Beating frequency and regularity provide additional information on temporal cardiac activity.
For example, omecamtiv mecarbil increased contraction strain while modifying contraction and relaxation kinetics, illustrating how changes in contractile amplitude and contraction dynamics can occur together without following identical concentration-response profiles.
Analyzing these complementary parameters helps identify compound-specific functional signatures and informs the selection of subsequent mechanistic experiments.
Relevance for cardiac efficacy and safety assessment
Quantitative assessment of cardiac contractility is relevant to several stages of drug development.
For cardiovascular efficacy studies, positive inotropic responses can help characterize compounds intended to modulate cardiac mechanical performance.
Changes in relaxation kinetics may also provide useful functional information when investigating compounds targeting diastolic or sarcomeric mechanisms.
For cardiac safety studies, negative inotropic responses may reveal drug-induced impairment of tissue contractility, including effects that are not captured by electrophysiological measurements alone.
The ability to quantify positive and negative inotropic effects within a standardized human cardiac microtissue workflow supports the investigation of both intended pharmacological activity and potential functional cardiac liabilities.
Disease-specific conclusions, including predictions of therapeutic benefit in heart failure, require appropriate disease models and additional validation.
Complementarity with 2D cardiomyocyte assays
Two-dimensional human iPSC-derived cardiomyocyte assays provide valuable information on cellular activity, electrophysiology, and drug-induced changes in cell motion.
Engineered 3D cardiac tissues offer a complementary experimental approach by introducing organized tissue geometry and defined mechanical boundary conditions.
In SmartHeart®, ring-shaped microtissues contract around a deformable hydrogel pillar, enabling tissue-level deformation measurements.
This configuration allows drug-induced mechanical changes to be quantified alongside spontaneous beating activity.
The results presented here demonstrate the ability of SmartHeart® to detect positive and negative inotropic responses across several pharmacological mechanisms.
However, this qualification study was not a direct comparison between SmartHeart® and matched 2D assays. Claims of superior sensitivity or predictive performance would require dedicated comparative experiments.
-
LIMITATIONS AND SCOPE OF INTERPRETATION
The results presented in this white paper support the fit-for-purpose qualification of the SmartHeart® Contractility Assay under the tested experimental conditions.
Several limitations should be considered when interpreting these findings:
Mechanical readouts: The core assay quantifies cardiac tissue deformation, contraction–relaxation kinetics, and beating activity from brightfield recordings. It does not directly measure intracellular calcium transients or action potentials.
Exposure duration: The qualification study used acute, sequential compound addition with a four-minute incubation before each acquisition. Delayed, cumulative, or chronic drug responses may require adapted protocols.
Tissue maturity: Experiments were conducted at Day 21 after seeding. Results may differ with changes in tissue composition, cell source, maturation time, or culture conditions.
Assay sensitivity: Detection thresholds depend on the experimental design, number of evaluable tissues, biological variability, and statistical analysis.
Mechanistic interpretation: Mechanical responses can be consistent with known pharmacological mechanisms without establishing those mechanisms independently.
Translational scope: Agreement with published pharmacological observations supports the biological relevance of the model but does not establish clinical predictive accuracy.
Complementary electrical pacing, electrophysiology, calcium-transient measurements, or longer exposure protocols may be incorporated into tailored study designs when scientifically justified. These extensions are not automatically covered by the qualification of the core contractility workflow.
-
CONCLUSION
The SmartHeart® Contractility Assay provides a quantitative approach to characterizing drug-induced inotropic effects in human 3D cardiac microtissues.
Across a panel of seven reference compounds representing different pharmacological mechanisms, the assay correctly identified the expected direction of five positive and two negative inotropic responses under the tested conditions.
Multiparametric analysis revealed distinct functional signatures involving contraction strain, beating frequency, and contraction–relaxation kinetics.
The assay also demonstrated reproducible concentration-response measurements and characterized readout-specific detection sensitivity within its qualified experimental design.
Together, these findings support SmartHeart® as a fit-for-purpose human cardiac microtissue platform for the investigation of drug-induced changes in cardiac contractility, with applications in cardiovascular pharmacology, efficacy research, and functional cardiac safety assessment.
-
FREQUENTLY ASKED QUESTIONS
-
REFERENCES
4Dcell (2026). SmartHeart – Performance Characterization and Fit-for-Purpose Qualification for Inotropic Compound Screening. Internal technical qualification report, September 8, 2026. [available on demand]
Abi-Gerges et al. (2020). Multiparametric Mechanistic Profiling of Inotropic Drugs in Adult Human Primary Cardiomyocytes. Scientific Reports, 10, 7692.
https://doi.org/10.1038/s41598-020-64657-2
Swenson et al. (2017). Omecamtiv Mecarbil Enhances the Duty Ratio of Human β-Cardiac Myosin Resulting in Increased Calcium Sensitivity and Slowed Force Development in Cardiac Muscle. Journal of Biological Chemistry, 292, 3768–3778.
https://doi.org/10.1074/jbc.M116.748780
Mamidi et al. (2017). Dose-Dependent Effects of the Myosin Activator Omecamtiv Mecarbil on Cross-Bridge Behavior and Force Generation in Failing Human Myocardium. Circulation: Heart Failure, 10, e004257.
https://doi.org/10.1161/CIRCHEARTFAILURE.117.004257
Nguyen et al. (2017). Adult Human Primary Cardiomyocyte-Based Model for the Simultaneous Prediction of Drug-Induced Inotropic and Pro-Arrhythmia Risk. Frontiers in Physiology, 8, 1073.
https://doi.org/10.3389/fphys.2017.01073
-
EXPLORE SMARTHEART® CARDIAC CONTRACTILITY TESTING
Discover how SmartHeart® can support your drug development program through quantitative measurement of inotropic and chronotropic effects in human 3D cardiac microtissues.
Explore the SmartHeart® Contractility Assay
Learn more about SmartHeart® human 3D cardiac microtissues
Share your compound's mechanism of action and experimental objectives with the 4Dcell scientific team.